


Laparoscopic Surgery
Laparoscopic surgery is a minimally invasive method in which the surgeon operates through small incisions and sees the internal organs magnified on a screen, instead of using the large incisions of open surgery.
Dr. Konstantinos M. Konstantinidis operated and taught the method in the USA as Director of the Surgical Clinic of Riverside Methodist Hospital. In 1991 he returned to Athens to create and direct the Department of Laparoscopic Surgery and Laser Applications of the Athens Medical Group, the first such department founded in Greece.
The department he founded and has directed ever since offers patients from all over Greece and abroad the most modern techniques, such as advanced laparoscopic and robotic surgery. He has also trained many dozens of surgeons in Greece and abroad.
What is laparoscopic surgery?
Laparoscopic Surgery is perhaps the most important development of General Surgery in the 20th century. The word laparoscopy comes from the ancient Greek words “laparo” which means belly and “scopy”, which means to see.
Thus, while open surgery is performed through large incisions in the abdomen so that there is direct vision of the patient’s organs, in laparoscopy the surgeon performs the operation through small incisions and magnifies the patient’s internal organs on a screen.
Laparoscopy is the examination of the peritoneal cavity with a telescope that is inserted into the abdomen through the abdominal wall after pneumoperitoneum formation.
Laparoscopic surgery is the performance of documented procedures in such a way that surgical injury during entry is smaller resulting in faster recovery of the patient.
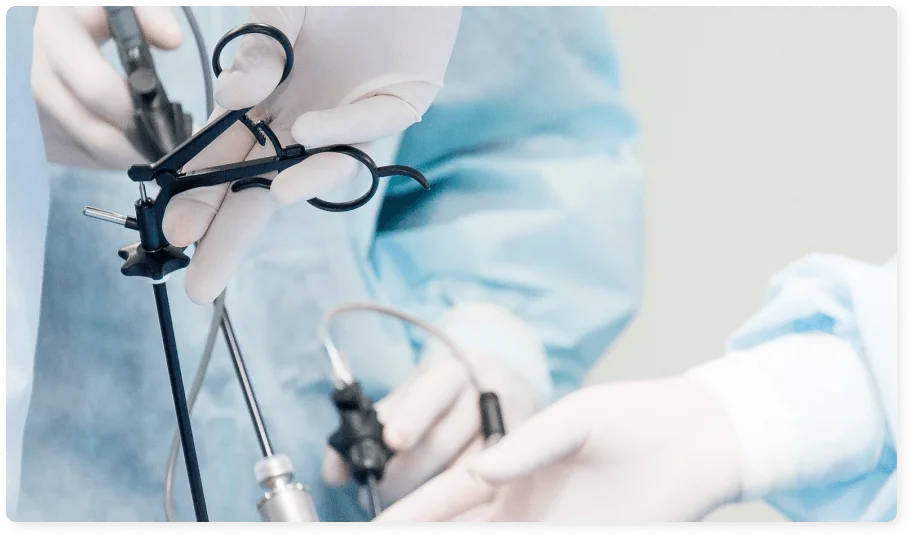
The surgical maneuvers are performed outside the patient’s body through laparoscopic instruments that allow the tissue preparation movements into the narrow spaces of the peritoneal cavity or other extraperitoneal spaces, under direct vision through a video camera and a monitor.
The laparoscopic method requires long-term training and experience. Robotic surgery is an evolution of conventional laparoscopy, the latter, despite its many advantages, having some limitations. However, robotic surgery also requires a good knowledge of the principles of laparoscopic surgery and that is why we consider it appropriate to refer to them. The latter is a matter of debate as to whether young surgeons should be trained directly in robotic or laparoscopic surgery, or whether they should first acquire the skill of conventional “open” surgery. We adopt Ash Tewari’s view that “when you have learned to perform surgery, you know how to operate in any way: open, laparoscopic, robotic or through natural holes.”

Do you want to know more about ?
Why choose Dr. Konstantinidis?
Dr. K. M. Konstantinidis and his team possess vast experience in the field of laparoscopic and robotic surgery.
Dr. Konstantinidis is the pioneer of Robotic Surgery in Greece and one of the leading figures internationally in the field, having performed the largest series of General Surgery operations in Europe with the innovative Da Vinci® robotic system.


How laparoscopic surgery developed
The vision of intervention through observation was fulfilled thanks to the evolution of both science and technology, with the use of fiber optics and video technology. Creating a three-dimensional image further expands the scope and prospects of laparoscopic surgery.
The history of laparoscopy
The idea of minimally invasive surgery is not novel. The use of tubes and dilators in medicine began in the early days of the civilizations in Mesopotamia and ancient Greece.
The beginnings of modern endoscopy date back to 1805, when Bozzini, a gynecologist from Frankfurt, used a candle as a light source to attempt to examine the vagina and female urethra through a thin tube.
In 1897 Nitze, a urologist from Berlin, in collaboration with Reinecke, an optician also from Berlin, and Leiter, a tool maker from Vienna, built the first cystoscope, with a lens system and platinum wire as the light source.
In 1901 Von Ott from St. Petersburg announced the first abdominal examination using a head mirror focusing on a dilator. A year later, Kelling, using a cystoscope and creating a pneumoperitoneum with filtered air, announced at a Hamburg conference the successful laparoscopy on a live dog.
In 1910, Jacobaeus, a surgeon from Stockholm, performed laparoscopy and thoracoscopy on a human using a cystoscope.
From 1920 to 1930, Kalk, the founder of the German School of Laparoscopy, designed many tools, promoted the spread of diagnostic laparoscopy in diseases of the liver and bile ducts, and paved the way for the development of surgical laparoscopy.
This was followed by the development of laparoscopy in gynecology by Palmer (France), Frangeheim and Semm (Germany), Steptoe (Great Britain) and Phillips (USA).
The evolution of fiber optics and the development of the lens system by the British physicist Hopkins in 1952, led to a rapid increase in the use of endoscopic and laparoscopic devices worldwide.
The sources of modern laparoscopic surgery can be found at the Kiel School in Germany under the direction of gynecologist Semm. This center developed and perfected most of the tools and introduced most of the laparoscopic gynecological procedures that are still performed today.
Although gynecologists have been using laparoscopy for several years, general surgery has been slow to follow suit. The first laparoscopically guided cholecystectomy was performed in an experimental model by Frimberger and colleagues in Germany in 1979. Semm and his team described the technique of laparoscopic appendectomy using a modified orthoscope and CO2 pneumoperitoneum in 1985.
A relatively recent technological development was the introduction of the computer chip camcorder in 1986, which sparked the development of laparoscopic surgery in its current form.
In 1987, Mouret in Lyon (France) was the first surgeon to perform a cholecystectomy on a human using specific laparoscopy equipment. The first published announcement of modern multiple intra-abdominal cholecystectomy was made by Dubois in Paris in 1989. Around the same time, the operation was performed by Perissat (in Bordeaux, France), Reddick (in Nashville, USA), Cuschieri and Nathanson (in Dundee, UK) and Berci (in Los Angeles, USA).
Since then, the application of laparoscopic techniques has spread rapidly in the various specialties of surgery. There is no doubt that many parameters of current equipment can and will be improved in the near future to facilitate this beneficial method of minimally invasive surgery.
Since the year 2000, the proliferation of robotic surgical systems has marked a new era in laparoscopic surgery, in which several of the limitations of classical laparoscopy are overcome.
What are the benefits of laparoscopic surgery?
Laparoscopic surgery provides significant benefits:
Minimal surgical injury
Quick recovery
Minor blood loss
Shorter hospitals stay
Lower treatment costs
Rapid return to work
Image magnification by 10-15 times and better lighting
Minimization of postoperative pain
Almost elimination of postoperative complications related to the surgery, such as perforation, rupture, hernia, chronic pain, etc.
Less respiratory and cardiovascular complications
Lower possibilities for postoperative adhesions
The surgical team is protected from passing on viral infections
Easier to treat patients in serious conditions
What are its applications?
Current applications of laparoscopic surgery have expanded to a wide range of operations, including both simple and specialized procedures, such as:
Laparoscopic cholecystectomy and bile duct examination in combination with intraoperative cholangiography, intraoperative galloscopy and intraoperative ultrasound
Laparoscopic appendectomy
Laparoscopic treatment of hernia (inguinal hernia, femoral hernia, abdominal hernia, etc.)
Laparoscopic treatment of gastroesophageal reflux with or without hiatal hernia and laparoscopic cardiomyotomy for the treatment of esophageal achalasia
Laparoscopic colectomy for the treatment of benign diseases of the colon (diversion, polyps, ulcerative colitis, etc.), as well as colon cancer
Laparoscopic treatment of morbid obesity with ring placement or other complex techniques (gastric bypass, etc.)
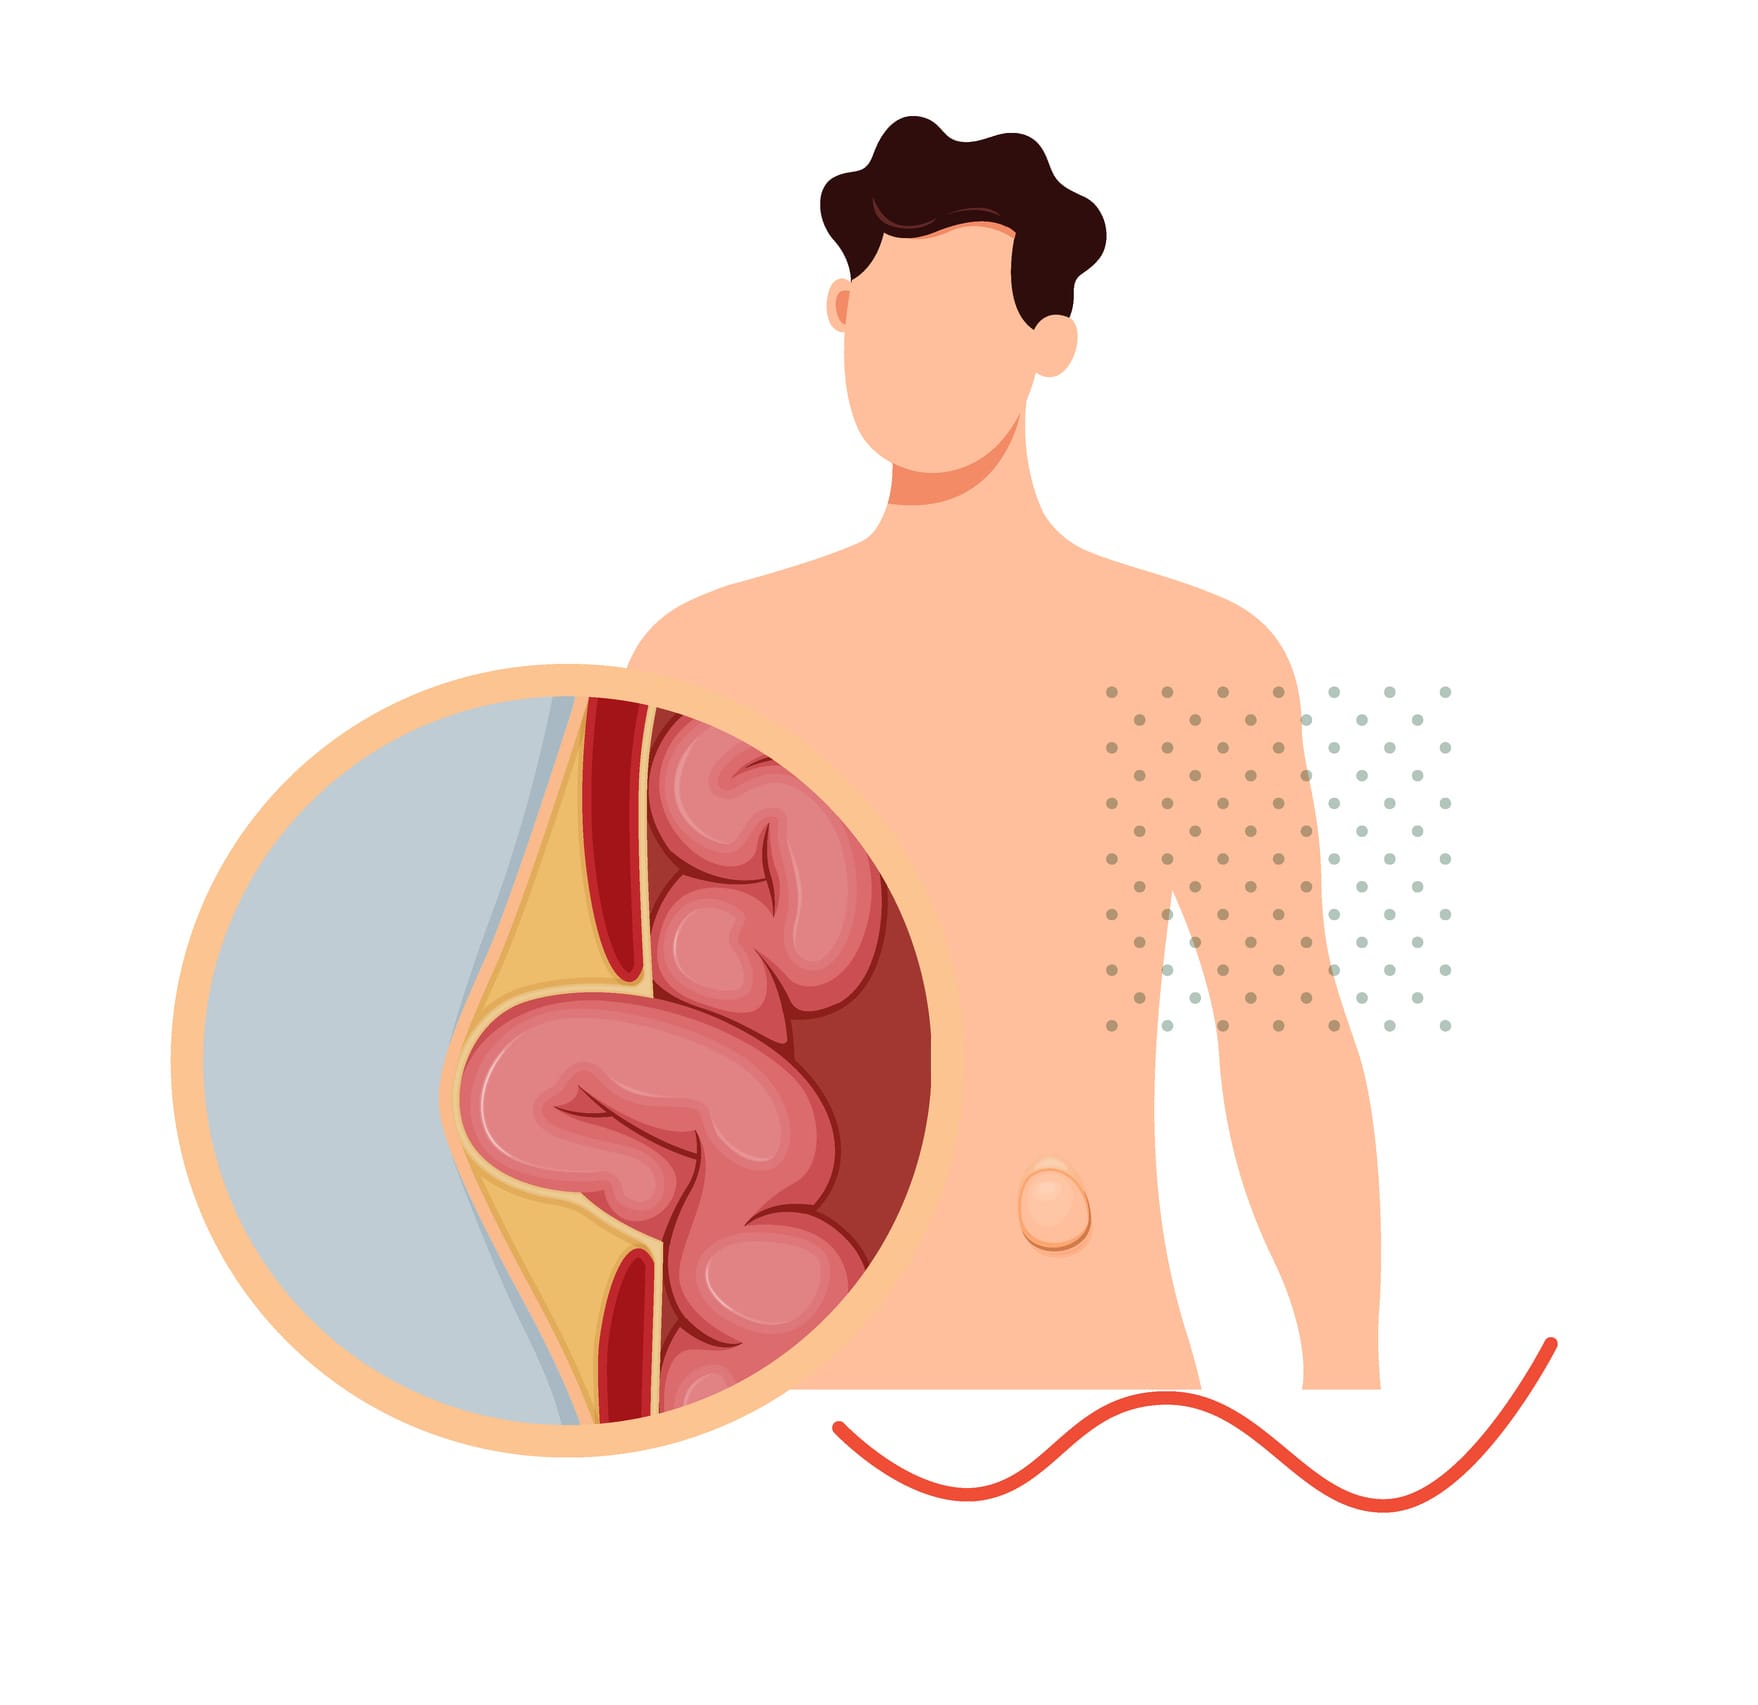
Laparoscopic treatment of intestinal obstruction / adhesions
Laparoscopic treatment of benign & malignant breast diseases
Laparoscopic treatment of gynecological diseases (endometriosis, pelvic adhesions, ovarian cysts, uterine fibroids, ectopic pregnancy, etc.) as well as laparoscopic hysterectomy
Laparoscopic oncology surgery for the staging or palliative treatment of cancer
Laparoscopy in acute abdomen (peritonitis) and injury
Diagnostic laparoscopy, most commonly for investigating abdominal pain, removing tissue or fluid for biopsy, etc.
Laparoscopic pancreatectomy
Laparoscopic gastrectomy
Laparoscopic treatment of gastroduodenal ulcer
Laparoscopic liver surgery
Laparoscopic adrenalectomy
Laparoscopic splenectomy
Laparoscopic pelvic lymph node dissection

What is enhanced recovery after surgery (ERAS protocol)?
Enhanced Recovery After Surgery (ERAS®) protocols were developed to shape a modern surgical culture with the patient at its centre.
Their goal is to minimise the impact of surgery on the patient, to preserve the normal function of the body and to optimise and accelerate recovery.
In particular, they include evidence-based techniques to minimise surgical trauma and postoperative pain, reduce complications, improve outcomes and shorten the hospital stay.
Enhanced recovery surgery (ERAS protocols) is a comprehensive, multidisciplinary approach that requires the participation and commitment of the patient, the surgeons, the anaesthesiologists, the nursing staff, the physiotherapists and the hospital management.
Initially, ERAS protocols resulted in many procedures becoming day-case procedures. Over time, and as experience grew, the principles of enhanced recovery were applied to increasingly complex procedures, to shorten the hospital stay and speed up the patient’s return to their pre-operative health and functionality.
ERAS® protocols are currently available for colorectal surgery, gynaecological and urological procedures, as well as for liver, pancreatic and breast surgery.
Enhanced recovery surgery opens new paths in patient care, creating a smooth transition from home and pre-operative preparation to surgery, the postoperative phase and hospital stay and, finally, the return home.
Frequently Asked Questions
Both methods are performed through small incisions. In laparoscopic surgery the surgeon handles the instruments directly on the patient, while in robotic surgery the surgeon sits at a surgical console, views the operating field on a screen and performs the operation by moving special controls. Robotic surgery is an evolution of laparoscopic surgery that overcomes several of its limitations. Read more about robotic surgery.
Among others, cholecystectomy, appendectomy, hernia repair, the treatment of gastroesophageal reflux and hiatal hernia, cardiomyotomy for oesophageal achalasia, colectomy for benign conditions and for colorectal cancer, adrenalectomy, splenectomy and procedures for gynaecological conditions. The full list is in the section “What are its applications?” above.
Thanks to the small surgical wound, postoperative pain is lower, discharge from hospital is earlier and return to work is faster than after open surgery. The exact time depends on the type of operation and the patient’s condition. Enhanced recovery (ERAS) protocols aim precisely at speeding up this return.
The laparoscopic method requires long training and experience, because the manoeuvres are performed with special instruments in narrow spaces, viewed through a camera and a screen. Dr. Konstantinidis has practised the method since his years in the USA and since 1991 has directed the first department of laparoscopic surgery founded in Greece.
At the Athens Medical Center, 3 Distomou St., Marousi. For an appointment you can call +30 210 61 07 165 or contact us.
